Introduction
Denture fabrication once meant physical impressions, manual wax-ups, and try-ins shipped back and forth between practice and lab. Many labs and practices still struggle with slow turnaround, remake costs, and inconsistent fit when that manual chain is the only option.
Digital denture technology connects intraoral scanning, CAD design, digital manufacturing, and file archiving into one workflow. The result is faster case movement, more repeatable fit, and archived designs you can remake without starting from scratch.
This guide is for dental labs, practices, prosthodontists, and manufacturing teams weighing digital adoption. It covers how the workflow works, technology options on the market, realistic benefits and limits, and how to plan implementation.
One clarification up front: "digital dentures" means an end-to-end process—not a single machine or material. Clinical suitability and final treatment decisions always stay with qualified dental professionals.
Key Takeaways
- Digital dentures unite scanning, CAD, and print, mill, or hybrid production in one workflow.
- Archived design files speed remakes and repairs when privacy controls stay in place.
- Printing prioritizes speed and material options; milling often delivers higher density and strength.
- Training, materials, and post-processing support drive adoption more than hardware alone.
What Is Digital Denture Technology?
Digital denture technology replaces or supplements physical impressions and manual wax-ups with a connected digital chain: scan, design, manufacture, and archive. Conventional dentures rely on stone models, manual tooth setup, and in-person try-ins at nearly every adjustment. Digital workflows move most of that work into software, though clinical evaluation still happens chairside.
Core Technologies in the Workflow
A digital denture workflow typically involves:
- Scanning - intraoral scanners or lab scanners capture oral anatomy, existing denture geometry, or physical impressions
- CAD design software - establishes tooth position, base contours, and occlusion
- CAM manufacturing - 3D printing or milling produces the physical prosthesis
- Digital articulation - simulates bite relationships virtually before manufacturing
- Electronic case records - store scans, approved designs, and manufacturing files for later reference
Three Terms That Aren't Interchangeable
These labels describe different steps and are not synonyms:
- Digitally designed — tooth arrangement and base created in CAD software
- 3D-printed — design manufactured layer by layer from a resin
- Milled — cut from a pre-polymerized puck or disc
A denture can be digitally designed and then produced by either printing or milling.
Digital workflows apply across multiple restoration types:
- Complete and partial dentures
- Immediate dentures
- Implant-supported overdentures
- Denture bases, teeth, try-ins, and working models
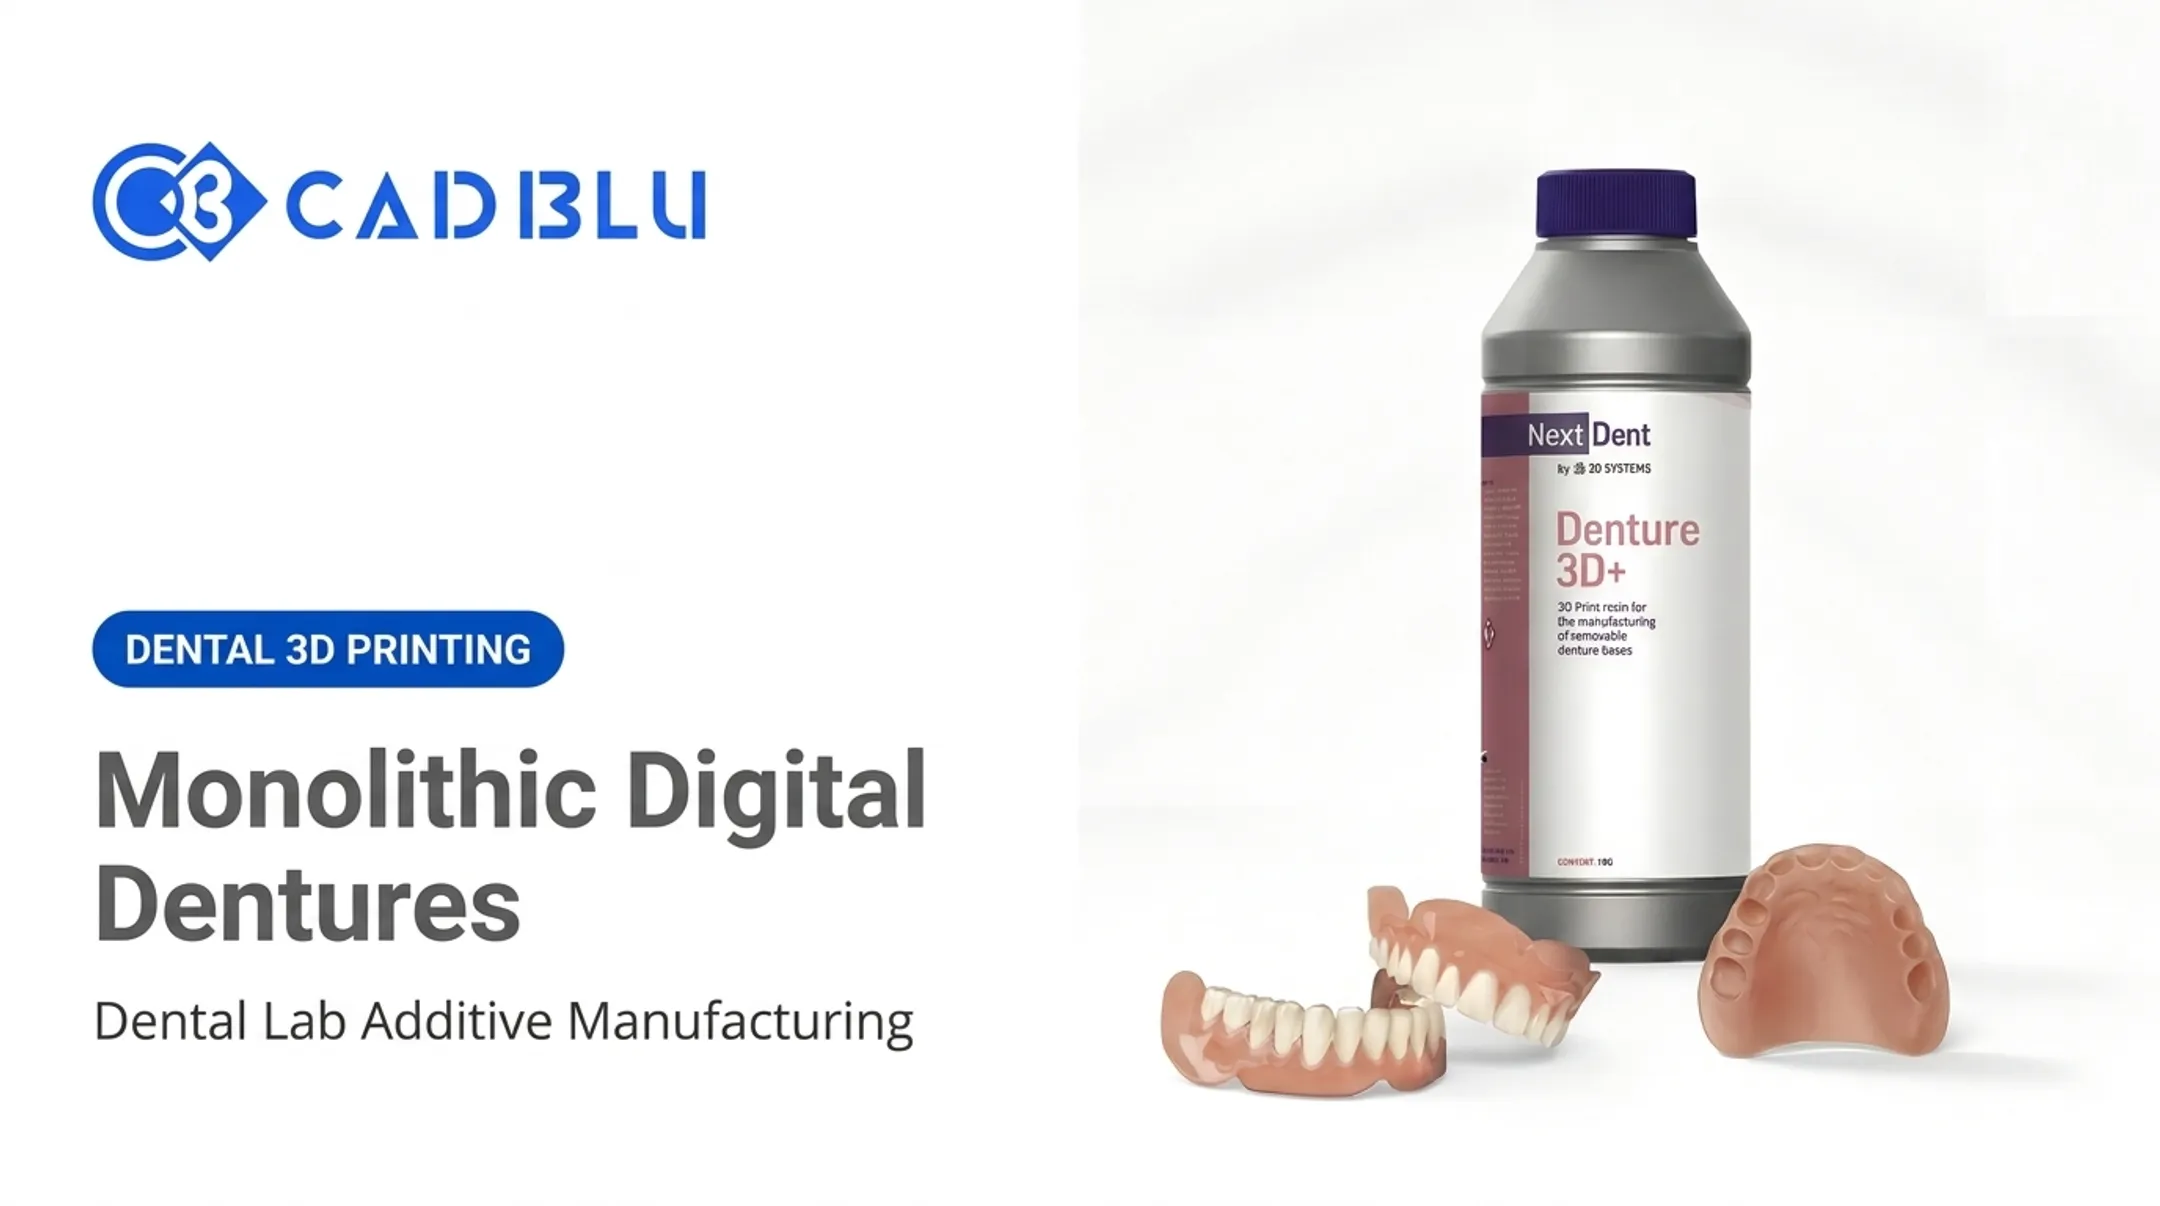
The NextDent 5100 platform, for example, supports orthodontic models, surgical guides, night guards, and both try-in and long-term dentures on one system, depending on the validated material.

How the Digital Denture Workflow Works
Capturing the Case
The workflow starts with data capture. Common inputs include:
- Intraoral scans of the arches
- Scans of physical impressions
- Digitized bite records
- Implant positions and existing denture geometry, when relevant
Accuracy at this stage is non-negotiable. Poor bite registration or incomplete records create problems downstream that CAD editing can't fully fix later.
Designing in CAD
Once those records are imported, the case is cleaned and aligned in CAD software. Technicians set tooth position, base contours, occlusion, and border extensions from the clinical parameters captured upstream.
This is also where the lab and practice collaborate most: many teams review a virtual design together before anything is printed or milled.
Validating the Design
Before final manufacturing, many workflows print a wax try-in or tooth-positioning guide. That step checks vertical dimension of occlusion, esthetics, and phonetics—so the clinician can request changes while they are still low-cost to implement.
Manufacturing: Printing vs. Milling
- 3D printing builds the denture layer by layer from a compatible resin, then washing, post-curing, support removal, and finishing. NextDent's 300 system, for example, can print a full build of 15 arches in about 9 hours, with post-processing and shipment possible within 24 hours.
- Milling cuts the denture or component from a pre-polymerized puck, then finishes, assembles, and inspects it before delivery.
Quality Control and Archiving
Post-processing typically covers:
- Dimensional checks and fit verification
- Occlusal inspection
- Documentation of production parameters and material lot numbers
Secure digital archives support remakes or replacements later, but an older file must still be checked against the patient's current anatomy. A reproduced prosthesis always needs clinical inspection before delivery.
Labs and practices building this stack—scanning, CAD, printing or milling, materials, and support—often partner rather than assemble every piece alone. CAD BLU works with dental teams on equipment selection, workflow setup, materials, and OEM-certified repair as they scale digital denture production.
Key Technologies Used in Digital Dentures
3D Printing vs. Milling
| Factor | 3D Printing | Milling |
|---|---|---|
| Speed | Fast, batch production possible | Slower, typically one puck per unit |
| Material waste | Low | Higher (disc waste) |
| Labor | Lower, more automated | Higher, more manual finishing |
| Scalability | Easier to scale up | Harder to scale for volume |
| Strength | Depends on resin and post-cure | Often stronger in comparative testing |
A 2025 meta-analysis found milled denture bases showed the strongest overall mechanical profile, with printed-versus-milled flexural strength differing by roughly 1.1 MPa in milling's favor. That evidence is still mostly lab-based, not long-term clinical data—treat it as directional, not definitive.

Materials and Regulatory Considerations
Dental resins and pre-polymerized pucks need confirmed biocompatibility, a stated intended-use indication, and a validated curing or milling protocol.
In the US, denture base resins fall under FDA's Class II framework. That framework sets mechanical and biocompatibility testing requirements, including flexural strength minimums in FDA's 2022 guidance. Clearance is product-specific: a resin cleared for one indication is not automatically cleared for another.
Scanners and CAD Software
Scanner accuracy, scan strategy, and export compatibility all affect downstream design quality. When you evaluate CAD software, compare how well it supports:
- Tooth libraries
- Digital articulation
- Occlusal analysis
- Clinician-approval workflows
Some platforms, like 3D Sprint, also handle automatic part placement, support generation, and job-statistics reporting for print prep.
A Note on Silicone and Flexible Materials
Silicone soft liners, flexible partial-denture materials, and rigid full-denture bases are three separate material classes—not interchangeable options.
- Flexible thermoplastic bases may suit patients with PMMA allergies or limited mouth opening
- They generally show lower hardness and impact strength than rigid PMMA
Ask for clinical evidence before assuming a flexible or silicone-based material fits every denture type.
Benefits and Limitations of Digital Denture Workflows
What Digital Workflows Can Offer
- Stored files support consistent remakes and design reproduction
- Fewer analog steps streamline handoffs between practice and lab
- Digital shade matching and virtual tooth arrangement speed customization
- Case records and material traceability stay easier to maintain
A retrospective study of 60 edentulous patients found digital denture chairside time averaged 154 minutes versus 218 minutes for conventional dentures.
A separate randomized crossover study of 10 patients found no significant difference in appointment counts or satisfaction, so results still vary by workflow and sample size.
Practice-level results can look stronger when the setup is validated. Dr. Wahle at Greater Baltimore Prosthodontics found NextDent 5100 denture bases more accurate and precise than the practice's traditionally made prosthetics—a case-level outcome, not a universal benchmark.
What to Watch For
Digital adoption comes with real costs and constraints:
- Initial investment in scanners, printers, or mills
- Software and hardware learning curves for staff
- Resin handling, calibration, and post-processing labor
- File-management and data-security requirements
- Some complex cases still need analog or hybrid steps
Scan inaccuracies, incomplete records, or poor bite registration can undermine even the best CAD design. Technology improves the workflow, but it does not replace clinical diagnosis, professional judgment, or final fit and occlusion checks.
Implementing and Choosing the Right Digital Denture Setup
Start With a Workflow Audit
Before buying anything, map your current process:
- Case volume and denture types produced
- Current bottlenecks and outsourcing needs
- Turnaround expectations and staffing capacity
- Available space and team technical experience
Three Adoption Models
- Outsource — Send digital production to a qualified lab or service provider for the lowest capital cost and less day-to-day control
- Partial in-house — Add a scanner or printer on-site while outsourcing design, printing, or finishing steps you are not ready to own
- Full in-house — Run printing or milling, post-processing, and quality control as a complete internal production line

Matching Setup to Priorities
| Priority | Better Fit |
|---|---|
| High-volume repeatable production | 3D printing (batch capability) |
| Premium mechanical properties | Milling |
| Limited capital expenditure | Outsourcing or partial in-house |
| Maximum in-house control | Full in-house or hybrid production |
A hybrid model keeps scanning and design in-house, then routes cases to printing, milling, or an outside lab as needed. For many labs, that mix is the practical middle ground before a full single-path commitment.
Total Cost of Ownership
Look past the sticker price. Equipment like the NextDent 300 lists at roughly $72,000, while a compact system such as the NextDent 5100 runs closer to $10,995.
Build the full cost model around:
- Materials and resin or disc consumption
- Post-processing labor and finishing time
- Maintenance, training, and service contracts
Due-Diligence Questions
Before you sign with a supplier, confirm fit on materials, software, and support:
- Which materials are validated for the intended indication?
- Which file formats and software systems are supported?
- What is the service and repair response process?
- What training is included at installation?
- How is quality control documentation handled?
CAD BLU supports labs and practices that are building digital denture capacity in stages or as a full line. That includes:
- Commercial 3D printers, scanners, and CAD software
- Validated materials for dental workflows
- Installation plus OEM-trained repair support
- Turnkey setups or partial additions to an existing process
Frequently Asked Questions
What is the newest technology for dentures?
Today’s digital denture workflows combine intraoral or lab scanning, CAD design, and production by 3D printing or milling, often with automated design aids. Newest is not best for every case—match the workflow to the indication and material.
How much do 3D digital dentures cost?
Price depends on case complexity, materials, lab or chairside fees, and whether you produce in-house or outsource. Request an itemized quote; ballpark figures rarely reflect finishing, try-ins, or remakes.
Do the new silicone dentures really work?
Silicone soft liners, flexible bases, and rigid denture materials solve different clinical problems—they are not swap-in replacements for each other. Have a dentist or lab confirm the material is validated for the specific indication.
Are 3D-printed dentures better than traditional dentures?
3D-printed dentures often win on digital repeatability and faster turnaround when the case and material fit. Traditional workflows can still be the better choice for complex aesthetics, certain materials, or clinic preferences.
What equipment is needed to make digital dentures?
An in-house setup usually needs a scanner, CAD software, a validated 3D printer or mill, post-processing tools, and approved denture materials. Outsourcing design or production shrinks that list to whatever you still handle chairside or in-lab.